Category: Obstructive lung diseases

Born Later, Breathing Better? How Lung Function Has Changed Across Generations


Do people born more recently have better lung function than earlier generations?

A recent study using data from 28,569 adults across 34 countries in the Burden of Obstructive Lung Disease (BOLD) study found that people born in more recent decades generally had better lung function than those born earlier.

What did the analysis find?

Participants were born between 1902 and 1976 and had completed spirometry at recruitment. Across time the forced vital capacity (FVC), the forced expiratory volume in 1second (FEV1) and the ratio FEV1/FVC improved across birth cohorts.

Even after accounting for factors such as age, height, smoking, body weight, education, occupational exposures and previous tuberculosis, people born later continued to have higher lung function.

The findings were both seen in high-income countries (HICs) and low- and middle-income countries (LMICs), as well as among men and women and people with different smoking histories.
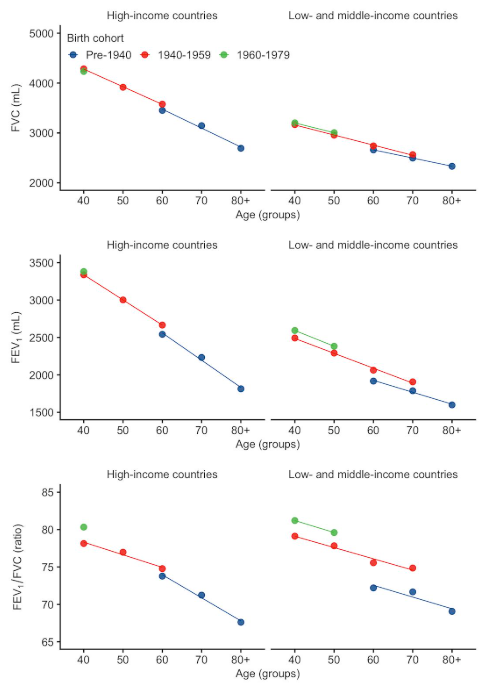


Figure 1 Birth cohort effects on post-­ bronchodilator lung function. Post-­ bronchodilator lung function by age group, country income group and birth cohort. Each marker represents the subgroup-­ specific mean of lung function values, and linear trendlines are shown. FEV1, forced expiratory volume in 1 s; FVC, forced vital capacity.

Why might lung function be improving?

Birth year itself does not make someone’s lungs healthier. Instead, it may reflect the conditions experienced by different generations.

However, our study cannot tell us which of these factors caused the differences. It shows an association between later birth year and higher lung function, not a direct cause-and-effect relationship.
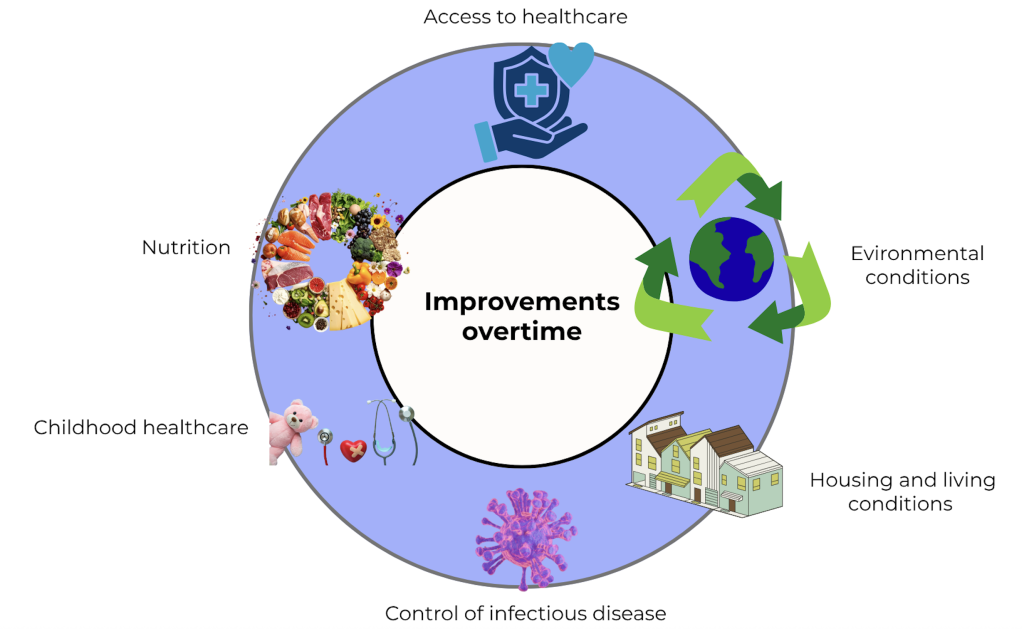
 

Figure 2. Plausible factors explaining the improvement in lung function over time.


Why does this matter?

Lung function tests are interpreted by comparing an individual’s results with expected values. If lung function has changed across generations, reference standards based on older populations may not always reflect what is typical for people born more recently.

What should we take away?

The findings highlight that lung health is shaped over a lifetime and may reflect improvements in health and living conditions across generations. More long-term research, particularly in LMICs is needed to understand what is driving these generational changes.

Want to know more? Read our paper now published in Thorax

Written in collaboration with Dr Jixuan Ma
Your job and your lungs: What a 10-year study found

We often think of smoking and air pollution when we talk about lung health. But what about the air we breathe for hours every day at work?

A recent analysis of data from the multinational Burden of Obstructive Lung Disease (BOLD) cohort study suggests that what we breathe at work, particularly dusts, fumes, gases and pesticides, may affect our lung health.

This analysis was based on 4,237 adults from the general population across 17 sites, mostly in low- and middle-income countries (LMICs), that were followed for a median of around 10 years. Each of them had their lung function measured using spirometry. By looking at the jobs each participant had throughout their life, we estimated their exposure at work to potentially harmful substances, including vapours, gases, dusts and fumes (VGDF), pesticides, solvents and metals each participant had been exposed at work.

So, what did we find?

People with greater occupational exposure to VGDF showed a larger decline over time in the ratio between two lung function parameters (FEV₁/FVC). This ratio tells us how easily air can be blown out of the lungs; falling values can be a sign of increasing airflow obstruction, which is typical of diseases such as asthma and chronic obstructive pulmonary disease.

Pesticides stood out too. Higher pesticide exposure was linked not only with a greater decline in lung function, but also with wheezing. Those in the high-exposure group had a much higher risk of wheezing compared with those with little or no exposure.

Interestingly, we did not find similar associations for solvents or metals, and the results were broadly similar in men and women.

Why does this matter?

For many people, occupational exposure isn’t occasional; it can mean breathing the same dusts, fumes or chemicals for decades. This may be particularly important in LMICs, where occupational exposure limits and workplace protections may be less consistently implemented or enforced.

While the study included a large and diverse multinational population, there are some limitations. Workplace exposures were estimated rather than directly measured, and lung function was measured only once at follow-up. There was also substantial loss to follow-up, partly due to the COVID-19 pandemic. These factors mean the findings should be interpreted with some caution, and further research is needed to identify which specific workplace exposures pose the greatest risk

The takeaway message: The air we breathe at work matters.

Smoking remains an important cause of chronic lung disease, but it isn’t the whole story. These findings reinforce the importance of reducing harmful workplace exposures and monitoring respiratory health, particularly among workers in high-exposure settings. Sometimes protecting lung health is not just about smoking; it’s also about making sure the places we work are safe to breathe in.

Read the full paper

The findings of this study were published in the peer-reviewed journal BMJ Open Respiratory Research. The article can be freely accessed and read here: https://bmjopenrespres.bmj.com/content/13/1/e004213

Lung Health – What’s Alcohol Got To Do With It?

The effects of alcohol on the liver, heart, and brain are well known. However, the impact of alcohol on lung health is often overlooked. Our new study shows that heavy drinking may contribute to early damage in the small airways of the lungs.

Using data from nearly 170,000 adults in the UK Biobank, we examined the relationship between weekly alcohol consumption and small airways obstruction. This condition is a subtle abnormality that can appear before asthma or chronic obstructive pulmonary disease (COPD). Because it rarely causes symptoms, this early damage is often missed in clinical settings.

After accounting for smoking, diet, socioeconomic status, and other influences, we have found that heavy drinkers were more likely to show signs of small airways obstruction than those who drink little or nothing at all. Strikingly, this association was also present among people who have never smoked, suggesting alcohol itself may contribute to early airway injury.

Moderate drinking did not significantly increase risk, but the likelihood of obstruction became clearer at very high levels of consumption. Although our findings cannot confirm causation, they add to growing evidence that alcohol may increase inflammation, weaken immune defences, and reduce the lungs’ ability to protect themselves.

These insights matter because small airways obstruction is both common and linked to the early stages of chronic lung disease. Greater awareness among clinicians and the public about alcohol’s potential role in respiratory health could support earlier prevention and intervention, complementing established risk factors like smoking.

As research continues, alcohol may deserve a more prominent place in conversations about long‑term lung health.

Check out the manuscript that has been published in CHEST and is available in open access here: https://dx.doi.org/10.1016/j.chest.2026.02.019.

Genes, Jobs, and Lungs: The Hidden Interplay Behind Respiratory Health

Same job, different health outcomes

Why do some people develop lung problems after years of workplace exposure while others do not? Two workers might share the same job, be exposed to the same harmful substances, yet only one goes on to develop lasting lung damage.

Exploring the early stages of lung disease

Small airways obstruction (SAO) is an early and often silent sign of chronic obstructive respiratory disease (COPD). SAO reflects the narrowing of the small airways of the lungs and can appear many years before it progresses to the large airways or presents with respiratory symptoms. Understanding these early signs of disease is important in preventing chronic lung disease later in life.

Combining genetics and workplace exposures

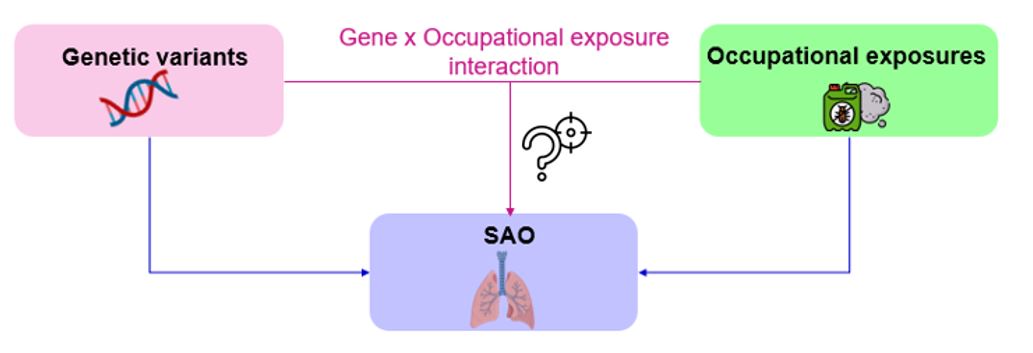
Using data from more than 147,000 UK Biobank participants, we conducted a genome-wide association study (GWAS) to identify genetic variants associated with SAO. We then investigated whether these variants interact with occupational exposures to modify the risk of SAO.


What are the key messages?

  • We identified 36 genetic variants associated with SAO.
  • Eight variants significantly interacted with occupational exposures.
  • Workers carrying two copies of the most common allele were more likely to develop SAO when exposed to pesticides, vapours, gases, dusts and fumes (VGDF), or metals, as compared to those with no copy of the common allele and not subjected to these occupational exposures.

In other words, some genes appear to amplify the harmful effects of occupational exposures.

Clues from lung tissue

Two genetic variants (rs9273529 and rs644045) were also moderately linked to gene expression in lung tissue, hinting at potential biological mechanisms. These may help explain how occupational and environmental agents trigger inflammation and damage in the lungs in some individuals but not all. However, future research is needed to confirm this.

 Why is this study important?

Our findings highlight the complex interplay between genes and environment in determining who develops SAO. Recognising these interactions could help identify workers who are more vulnerable to certain exposures and guide targeted prevention or monitoring strategies. However, this must be used ethically and responsibly. The path to better lung health lies not only in reducing harmful exposures but also in understanding how genes affect lung health.

Read Genes, Jobs, and Lungs: The Hidden Interplay Behind Respiratory Health in full

Geographical variation in lung function

Lung function varies across countries and within regions

Measurements of lung function are used by medics to help decide whether someone has a respiratory disease or not. These measurements are usually compared against population reference values. However, sometimes it is difficult to say if a person with lung function below the expected values for their age, sex, and height really have a disease or are part of a disadvantaged group whose lungs did not grow as much as expected.

Using data from adults in the multinational Burden of Obstructive Lung Disease (BOLD) study, we estimated how far certain measures of lung function, that is the forced vital capacity (FVC) and the forced expiratory volume in one second (FEV1) to FVC ratio (FEV1/FVC), vary between and within world regions. We made this using data from people who have never smoked, do not have respiratory symptoms of disease and have not been diagnosed with a respiratory disease.

We found that the FVC in relation to age and height varies geographically, but that there is no geographical variation in the FEV1/FVC ratio.

The low values of FVC in some world regions should not be considered optimal as they may well be associated with increased mortality (more on this here).

This manuscript has been published in Pulmonology and is available in open access here: doi.org/10.1080/25310429.2024.2430491.


Unmasking the threat of small airways obstruction

Tiny Airways, Big Impact

The damage of the small airways of the lungs can result in inflammation, structural changes, and increased airway resistance. This is a common characteristic of chronic respiratory diseases such as asthma or chronic obstructive pulmonary disease (COPD). While the small airways of the lungs may not be the star of the show, they are a crucial part of the lung health story.

Spirometry: The Lung Detective

Small airways obstruction (SAO) can be detected using spirometry. Traditionally, the mean forced expiratory flow rate between 25% and 75% of the forced vital capacity (FEF25-75) is the preferred parameter. However, novel parameters such as the forced expiratory volume in 3 seconds as a ratio of the forced expiratory volume in 6 seconds (FEV3/FEV6), have proven effective at detecting SAO.

We know that chronic respiratory diseases are leading causes of mortality around the world. Can SAO, even without ticking all the boxes for a doctor diagnosis of respiratory disease, predict death?

The big UK Biobank Study: What did we find?

We analysed the data of over 250,000 participants from the UK, who had high quality spirometry, and found some novel results:

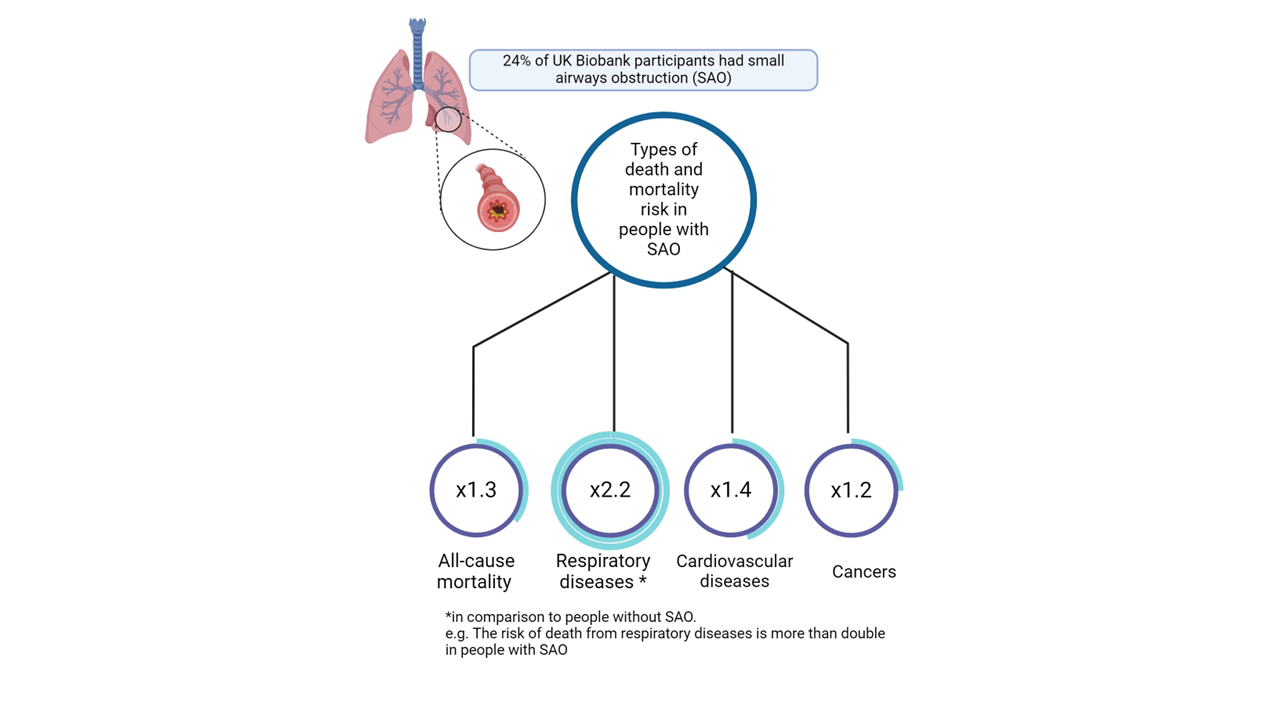
  • About 24% of participants had SAO. Among these, about 10% had isolated SAO, meaning their small airways were obstructed, but their larger airways were not.
  • People with SAO had increased risk of death from all causes, including respiratory diseases, cardiovascular diseases, and cancers. The risk was especially high for respiratory diseases, with more than double compared to those without SAO.
  • Even without respiratory disease (isolated SAO), the mortality risk was increased for cardiovascular diseases and cancers. Importantly, these findings were also true among people who have never smoked, indicating that SAO itself, regardless of smoking, is a critical factor.

Why should we care?

  1. Early Detection: Catching SAO early could be crucial in preventing more severe lung diseases later in life.
  2. Lifestyle Factors: Smoking is a big no-no for lung health, but even people who have never smoked can have SAO. This is likely to be caused by other factors.

While the UK Biobank cohort’s lack of representativeness and the relatively short follow-up period pose limitations, the study’s large sample size adds significant weight to the findings. Future research should aim to replicate these results in more diverse populations and explore the underlying mechanisms linking SAO to increased mortality.

Take home message.

Understanding and detecting SAO can give us a head start in managing chronic respiratory diseases such as COPD and asthma. Ultimately, this can aid to reduce respiratory morbidity worldwide. The findings of this study were published in the peer-reviewed journal CHEST. The article can be freely accessed and read here: https://doi.org/10.1016/j.chest.2024.04.016

Cough! Cough! Cough!

Chronic cough is a common respiratory symptom that affects the life of millions of people

Coughing on most days, without having a cold, for several months is one of the most common reasons why people book an appointment with their GP. Chronic cough is bothersome and has been linked to poorer health in people without obvious disease. However, the prevalence of – that is the proportion of people with – chronic cough and its associated risk factors are not well known in different regions of the world.

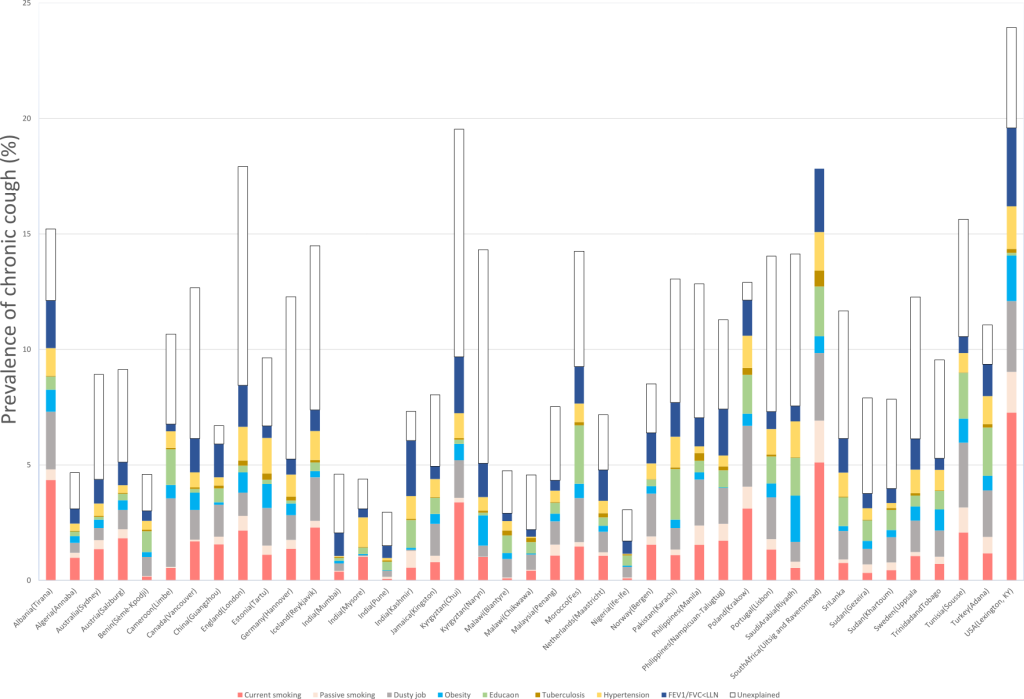
Using data from adults in the multinational Burden of Obstructive Lung Disease (BOLD) study, we estimated the prevalence of chronic cough in 41 locations from 34 countries around the globe and identified the factors that are more likely to determine the occurrence of chronic cough. We found a wide variation in the proportion of people with chronic cough across the different study locations – from 3% in Pune (India) to 24% in Lexington, KY (United States of America). Perhaps not surprisingly, tobacco smoking and working in a dusty job were the main risk factors for chronic cough. We identified other factors such as passive smoking, having had tuberculosis, being obese, having a low level of education and having hypertension.

Chronic cough population attributable risk for several factors across 41 sites of the BOLD study.


Despite our findings, in many locations, we still cannot explain all of the prevalence of this chronic cough.

This manuscript has been published in eClinicalMedicine and is available here: doi.org/10.1016/j.eclinm.2024.102423. This work was conducted as part of the PhD thesis of Hazim Abozid.

Spirometric assessment of the small airways, clinically useful after all?

Chronic obstructive pulmonary disease (COPD) is a common illness of the lungs, and one of the leading causes of death globally, particularly in the poorest countries in the world. Chronic airflow obstruction (CAO) is a key characteristic of a COPD diagnosis. It is identified using a lung function test called spirometry and reflects a reduction in the flow of air through the airways, which is present even after taking inhaled medication.

In early COPD, inflammatory changes occur in the small airways. These are airways less than 2mm in diameter. Their small size makes it easier for noxious particles and gases, such as tobacco smoke, to collide with their walls, meaning they are particularly susceptible to damage. This presents an opportunity for the early detection and treatment of COPD if lung function tests can be used to identify changes in the small airways before they progress to more severe disease.

Isolated small airways obstruction (SAO) reflects a reduction in the flow of air through the small airways, measured using spirometry. We have previously shown that isolated SAO is common globally, and what’s more, individuals with isolated SAO are more likely to have respiratory symptoms than those with otherwise normal lung function. We have now conducted a further study to investigate whether individuals with isolated SAO are more likely to progress to CAO over time and have a greater decline in lung function than the rest of the population. We used data from 3957 participants of the multinational Burden of Obstructive Lung Disease (BOLD) study. Participants were from 18 sites across the world.  At their baseline visit, participants performed spirometry before and after inhalation of a bronchodilator, which is a medication designed to open the airways, and completed a health questionnaire. They repeated the same measurements at a follow-up visit.

After an average of 8 years of follow-up, we found that individuals with isolated SAO were 2 to 3 times more likely to progress to CAO and had lower lung function at follow-up compared to those with normal lung function. This was true in both males and females, even in those who had never smoked. We also found that isolated SAO is better than basic information such as smoking history, age, sex, and body mass index (BMI) to predict future CAO. To confirm these findings, we replicated our research using data from the UK Biobank study and found similar results.

We have shown that using spirometry to assess small airways function can identify those who are at risk of developing COPD, who would be classed as having normal lung function using current criteria. This has implications for the early intervention and prevention of a disease that is associated with significant morbidity and mortality globally.


The manuscript published in BMJ Open Respiratory research is available here: http://dx.doi.org/10.1136/bmjresp-2023-002056

The Burden of Obstructive Lung Disease cohort

The BOLD study’s past and present

The Burden of Obstructive Lung Disease (BOLD) cohort is a large, multinational, prospective study of chronic respiraWorld map showing sites where the large multinational prospective BOLD study was conducted.tory disease. It started with the intention to measure the prevalence, risk factors, and impact of chronic obstructive pulmonary disease (COPD) in different populations around the world. COPD is a common and serious lung condition that causes breathing difficulties, coughing, wheezing, and reduced quality of life. It is estimated that COPD affects around 300 million people worldwide and is a leading cause of death globally.

The BOLD study has been a reference in the study of COPD because of its strengths:

• wide coverage of world regions and ethnic groups;

• large sample of representative population-based data;

• use of a standardised protocol, including the same questionnaires and same model of machine to test lung function, across study sites;

• centralised training and certification of interviewers and spirometry technicians. The quality of the data was monitored throughout the study, and re-training of staff was carried out if necessary;

• high quality of lung function measurements made before and after administration of a bronchodilator, with centralized quality control and assessment of all spirometry curves.

The BOLD cohort is still ongoing and will continue to provide important data and insights for the prevention, diagnosis, and management of COPD. More details about the past and present BOLD cohort can be found on the study’s website and in the profile published in the International Journal of Epidemiology (https://doi.org/10.1093/ije/dyad146).

Spirometric small airways obstruction (SAO) is associated with clinically important outcomes

People with obstructive lung diseases, such as asthma and COPD, commonly report respiratory symptoms, including shortness of breath, chronic cough, chronic phlegm, and wheezing.  Small airways disease is an important feature of both conditions, where the airways of the lungs that are less than 2mm in diameter become narrowed due to inflammation. Damage to the small airways is thought to precede the development of more severe lung disease. Therefore, the measurement of small airways function has implications for early detection and prevention of disease. Spirometric small airways obstruction (SAO) is a term used to describe obstruction of the small airways detected using a lung function test called spirometry. We conducted a study to investigate whether people with SAO are more likely to report respiratory symptoms, have a history of cardiometabolic disease, and a lower quality of life, even in the absence of established lung disease. We used data from 21,934 participants of the multinational Burden of Obstructive Lung Disease (BOLD) study. All participants performed spirometry before and after inhalation of salbutamol, which is a medication designed to open the airways. Participants completed a questionnaire which enabled us to collect information on their history of shortness of breath, chronic cough, chronic phlegm, and wheezing, as well as cardiovascular disease, hypertension, and diabetes. They also provided us information about their physical and mental quality of life.

We found that approximately 1 in 5 participants had SAO. Participants with SAO were 2-3 times more likely to report shortness of breath, chronic cough, chronic phlegm, and wheezing compared to those without SAO. In addition, we found that participants with SAO were approximately 30% more likely to have a history of cardiovascular disease but not diabetes or hypertension. We also found that physical and mental quality of life were lower in individuals with SAO. These results were also true in people who had never smoked.

We also investigated whether these findings were true among study participants with SAO but with ‘normal’ lung function and, in general, they were. The main difference was that these participants’ quality of life was unaffected

Although the spirometry parameters used to define SAO have long been considered of little use clinically, we have shown that spirometric SAO is not only common in general populations but is associated with outcomes of clinical interest. Further studies are needed to replicate our findings, as well as to investigate whether those with SAO are more likely to develop more serious lung disease in later life.


The manuscript published in Respiratory Research is available here: https://doi.org/10.1186/s12931-023-02450-1