Category: General Pathology

Patterns of Necrosis

Why the pattern matters.

The pattern of necrosis is a clue to why the tissue died. There are six patterns worth knowing. Five are morphologically distinct; the sixth, gangrene, is a clinical term that combines them.

Whatever the pattern, dead cells show the same nuclear changes, in sequence:

  • Pyknosis: the nucleus shrinks and becomes dense and dark
  • Karyorrhexis: the pyknotic nucleus fragments
  • Karyolysis: the nucleus fades as its DNA is digested

The cytoplasm becomes more eosinophilic (pinker), because it loses RNA and its proteins denature.

The six patterns

Coagulative necrosis

  • Where: infarcts in any solid organ except the brain, e.g. heart, kidney, spleen. Some toxic injuries also cause it, e.g. in renal tubules.
  • Cause:
  • Mechanism: acidosis denatures structural proteins and the cell’s own enzymes. As a result, the dead cell isn’t digested, and its outline survives for days.
  • Gross: firm and pale, often wedge-shaped. Infarcts in organs with a dual or loose blood supply (lung, bowel) are haemorrhagic and red.
  • Micro: architecture and cell outlines are preserved (“ghost cells”). The cytoplasm is hypereosinophilic, and nuclei show pyknosis, karyorrhexis or karyolysis. Neutrophils arrive at the edge, then macrophages.

Liquefactive necrosis

  • Where: bacterial (and some fungal) infections, i.e. abscesses. Also infarcts in the brain.
  • Cause and mechanism: the dead tissue is digested by enzymes. In an abscess, these come mainly from neutrophils. In the brain, they come from microglia and macrophages. The brain is rich in lipid and has almost no supporting connective tissue, so it liquefies easily instead of coagulating.
  • Gross: abscess: soft, creamy yellow pus. Brain infarct: soft and liquefied at first, then a fluid-filled cyst.
  • Micro: abscess: sheets of neutrophils and cell debris, with no preserved architecture. Brain infarct: foamy macrophages full of lipid, then a cystic cavity lined by reactive astrocytes (gliosis).

Caseous necrosis

  • Where: Also some fungal infections, e.g. histoplasmosis and coccidioidomycosis.
  • Mechanism: cell-mediated (type IV) hypersensitivity to the organism. T-cells activate macrophages, which form granulomas to contain the infection; the necrosis is a by-product of this response.
  • Gross: white, soft, crumbly, cheese-like (“caseous”) material.
  • Micro: amorphous, granular, eosinophilic debris. Unlike coagulative necrosis, the architecture and cell outlines are completely lost. It sits at the centre of a granuloma: epithelioid histiocytes, Langhans-type multinucleate giant cells and a rim of lymphocytes. Ziehl–Neelsen staining may show acid-fast bacilli.

Fat necrosis

  • Where: two settings. Enzymatic fat necrosis occurs in acute pancreatitis, in and around the pancreas. Traumatic fat necrosis occurs mainly in the breast, after injury or surgery; it can mimic carcinoma on palpation and imaging.
  • Mechanism: in pancreatitis, activated lipases released from pancreatic acinar cells split the triglycerides in fat cells. The free fatty acids then bind calcium to form soaps (saponification).
  • Gross: chalky white areas (calcium soaps). Traumatic fat necrosis forms a firm, irregular lump.
  • Micro: shadowy outlines of dead fat cells, with a basophilic (bluish) tinge from the calcium deposits. Surrounding inflammation includes foamy macrophages and, later, fibrosis.

Fibrinoid necrosis

  • Where: vessel walls. Causes include immune-mediated vasculitis (e.g. polyarteritis nodosa, the type III Arthus reaction) and malignant hypertension, which is not immune-mediated.
  • Mechanism: the vessel wall is damaged, and plasma proteins, including fibrin, leak into it. In vasculitis, immune complexes are also deposited there.
  • Gross: usually too small to see.
  • Micro: the vessel wall is replaced by bright pink, smudgy, amorphous material that resembles fibrin, hence “fibrinoid”.

Gangrenous necrosis

  • What it is: not a distinct pattern, but a clinical term for necrosis of a whole body part. It is used so often that it is worth knowing.
  • Where: usually the lower limb or digits (e.g. peripheral vascular disease, diabetes). Also bowel, e.g. volvulus or a strangulated hernia.
  • Dry gangrene: coagulative necrosis from loss of blood supply. The part is black, shrunken and mummified, with a sharp line of demarcation from living tissue.
  • Wet gangrene: bacterial infection is superimposed, adding liquefactive necrosis. The part is swollen, soft and foul-smelling, and the demarcation is poor. It spreads and can cause sepsis.
  • Gas gangrene: a form of wet gangrene caused by Clostridium perfringens. Gas in the tissue causes crepitus.
  • Colour: the black colour comes from haemoglobin breakdown products (iron sulphide).

At a glance

Pattern Classic setting Mechanism Gross Micro Architecture preserved?
Coagulative Infarct of heart, kidney, spleen Ischaemia; proteins and enzymes denature Firm, pale, wedge-shaped (haemorrhagic in lung, bowel) Ghost cells, hypereosinophilic cytoplasm, nuclear loss Yes
Liquefactive Abscess; brain infarct Enzymatic digestion (neutrophils; microglia and macrophages in brain) Pus; soft brain, then cyst Neutrophils and debris; foamy macrophages, then cyst (brain) No
Caseous Tuberculosis; some fungi Type IV hypersensitivity, granuloma formation White, crumbly, cheese-like Amorphous granular debris in a granuloma with giant cells No
Fat Acute pancreatitis; breast trauma Lipases release fatty acids, which bind calcium (saponification) Chalky white areas; firm lump (breast) Ghost fat cells, basophilic calcium, foamy macrophages Partly (fat cell outlines)
Fibrinoid Vasculitis; malignant hypertension Plasma proteins and fibrin (± immune complexes) leak into vessel wall Usually not visible Bright pink, smudgy vessel wall No
Gangrenous Lower limb, digits, bowel Ischaemia (dry) ± infection (wet) Black and mummified (dry); swollen and foul (wet) Coagulative (dry); coagulative plus liquefactive (wet) Dry: yes; wet: no

Neuro-endocrine Tumours ( in less than 500 words)

These tumours arise throughout the body but the gastro-intestinal tract (especially the appendix and rectum), followed by the lung (bronchus), are the commonest sites.
The frequency in these sites reflects the relatively large number of neuro-endocrine cells normally found there. Similarly, in the pancreas, which is another common site for neuro-endocrine tumours (NETs), are commoner in the tail than the head because the Islets of Langerhans are present in a higher density in the tail.

NETs were previously called carcinoid tumours but now the term neuro-endocrine tumours is now preferred except in the lung where the original term is still used.

NETs are graded (1-3) according to their rate of proliferation of the tumour cells which can be assessed either by counting mitoses or using an immunohistochemical marker (Ki-67). The higher the rate, the higher the grade and the greater the risk of metastatic disease although there is no clear cut-off level. The tumours in the appendix and rectum almost always never metastasize. Small intestinal NETs are especially likely to do so. Challengingly the secondary tumours may be larger than the primary they arise from which can make it difficult to identify the latter.

In the gastro-intestinal tract the tumours are usually submucosal although they may ulcerate. They may invade through the wall and may reach the peritoneal surface. They are often associated with a marked desmoplastic reaction. Multiple tumours may be seen; in the ileum 40% are multiple. Spread is to regional lymph nodes and the liver.

Histologically, NETS, are composed of relatively uniform cells arranged, in cords or nests, and have granular cytoplasm. The granules contain a protein, chromogranin, which can be used as an immunohistochemical or serum marker for these tumours.

NETs may secrete a wide range of hormones. The carcinoid syndrome is associated with the secretion of serotonin usually by git tumours. It is characterized by diarrhoea and bronchospasm and may be associated with fibrosis involving the right-hand side of the heart which can produce distortion of the valves. It is only seen in tumours which have spread to the liver as otherwise the serotonin is broken down in the liver.

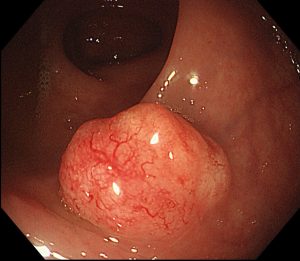
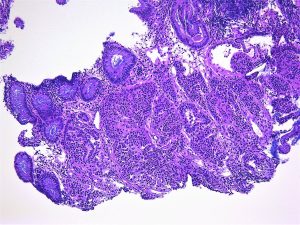
Below is are images of a rectal carcinoid tumour (made available by the excellent @Patholwalker).


Undergraduate Pathology: The Pathology of Neoplasia

This is the text of the first year cellular pathology course lecture which I am giving tomorrow.
I hope that it might act as a focus for interaction with the students.

The Pathology of Neoplasia

Tumour: Any kind of massforming lesion. May be neoplastic (see below), hamartomatous (see below) or inflammatory (e.g. nasal polyps).

Neoplasm: The autonomous growth of tissue which have escaped normal constraints on cell proliferation.
Neoplasms may be either benign (remain localised) or malignant (invade locally and/or spread to distant sites).

Cancers are malignant neoplasms.

Hamartomas are localised benign overgrowths of one of more mature cell types e.g. in the lung. They represent architectural but not cytological abnormalities. For example: lung hamartomas are composed of cartilage and bronchial tissue.

Heterotopias are normal tissue being found in parts of the body where they are no normally present. For example: pancreas in the wall of the large intestine.

Important to note that many malignant tumours rarely cause death (especially skin cancers) and that some benign tumours do kill (usually because of their location, e.g. the brain)

Classification of neoplasms

The primary description of a neoplasm is based on the cell origin and the secondary description is whether it is benign or malignant.

For example, tumours of cartilage are either chondromas (if benign) and chondrosarcomas (if malignant.) The “chondro” stem means derived from cartilage the suffix “oma” means a benign tumour and the suffix ”sarcoma” means a malignant (soft tissue) tumour.

Type of epithelium Benign Tumour Malignant Tumour Example(s)
Squamous Squamous epithelioma or papilloma Squamous cell carcinoma Skin, oesophagus, cervix,

Glandular Adenoma Adenocarcinoma Breast, colon, pancreas, thyroid
Transitional Transitional papilloma Transitional cell carcinoma Bladder

Type of connective tissue Benign Tumour Malignant Tumour Example(s)
Smooth muscle Leiomyoma Leiomyosarcoma Uterus, colon
Bone Osteoma Osteosarcoma
(Osteogenic sarcoma) Arm, leg

Haematological neoplasms Benign Tumour Malignant Tumour Example(s)
Lymphocytes Extremely uncommon Lymphoma Lymphoma
Stomach
Bone marrow Extremely
uncommon Leukaemia Acute lymphoblastic leukaemia,
Chronic myeloid leukaemia

Teratomas

These are tumours derived from germ cells and can contain tissue derive from all three for 3 germ cell layers. They may contain mature and / or mature tissue and even cancers.
Malignant tumours with the suffix “oma”:

1. (Malignant) Lymphoma
2. (Malignant) Melanoma
3. Hepatoma (better called liver cell cancer).
4. Teratoma (not all, see above)

What are the differences between benign and malignant tumours?

1. Invasion: This means direct extension into the adjacent connective tissue and /or other structures e.g. blood vessels. This is what distinguishes dysplasia/ carcinoma in situ from cancer (see next lecture).
2. Metastasis: This means spread via blood vessels etc (see below) to other parts of the body.
NB All malignant tumours have the capacity to metastasise although they may be diagnosed before they have done so
3. Differentiation: This means how much do the cells of the tumour resemble the cells of the tissue it is derived from.
Tumour cells tend to have larger nuclei (and hence a higher nuclear-cytoplasmic ratio) and more mitoses than the normal tissue they are derived from. They may have abnormal mitoses (e.g. tripolar) and marked nuclear pleomorphism (variability in nuclear size and shape).
4. Growth pattern: This means how much does the architecture of the tumour resembles the architecture of the tissue it is derived from.
Tumours have less well defined architecture than the tissue they are derived from.

It is important to note that benign tumours may become malignant.

By which routes do tumours spread?

1. Direct extension. This is associated with a stromal response to the tumour. This includes fibroblastic proliferation (“ a desmoplastic response”), vascular proliferation (angiogenesis) and an immune response.
2. Haematogenous (via blood vessels). The blood vessels usually invaded are the venules and capillaries because they have thinner walls. Most sarcomas metastasise first via the blood vessels.
3. Lymphatic (via lymphatics to lymph nodes and beyond) The pattern of spread is dictated by the normal lymphatic drainage of the organ in question. Most epithelial cancers metastasise first via the lymphatics.
4. Transcoelomic (seeding of body cavities). The commonest examples are the pleural cavities (for intrathoracic cancers) and the peritoneal cavities (for intra-abdominal cancers)
5. Perineural (via nerves) This is an underappreciated route of cancer spread.

How do we assess tumour spread?

1. Clinically
2. Radiologically
3. Pathologically

How do we describe tumour spread (stage)?

T= Tumour: the tumour size or extent of local invasion
N= Nodes : number of lymph nodes involved
M = Metastases: presence of distant metastases

This is called the TNM system and the details are different for each kind of cancer

Grade = how differentiated is the tumour (see Differentiation, above)?
Stage = how far as the tumour spread (see TNM above)?

In terms of tumour prognosis, Stage is more important than Grade.

Benign Vascular Tumours

These are common but remember that a tumour is just a swelling and they are not all neoplastic.
Capillary haemangiomas are composed of small blood vessels with inconspicuous lumina. They occur in all organs but particularly come to notice when they involve the skin. A “port wine stain” and a “strawberry mark” are examples of these. The latter initially grow rapidly, soon after birth, and then may regress completely, usually by 10 years. Whether they should be considered as true neoplasms is not clear.
Angiomas may, also, be seen in the placenta (chorangiomas) and, because of the increased blood flow, cause fetal heart failure.
Following trauma some patients develop pyogenic granulomas. This is sometimes called a lobular haemangiomas because of the lobular arrangement of the blood vessels in them. This is a reactive not and not a neoplastic process and is commoner in pregnancy.
Bacillary angiomatosis is another non-neoplastic vascular proliferation that is most commonly seen in association with AIDS and which is due to infection with Bartonella.
Unlike capillary haemangiomas, cavernous haemangiomas, contain prominent vascular spaces containing blood. They carry a significant risk of rupture and bleeding and hence of intracerebral haemorrhage, when they occur in the brain, or intraperitoneal haemorrhage, when they occur in the liver
Vascular hamartomas (malformed) blood vessels may be seen in a number of syndromes such as the von-Hipple-Lindau Disease and the Sturge-Weber Syndrome.
Glomus tumours, which are derived from glomus bodies (which are in the skin, are composed of an arterio-venous shunt and are involved in temperature regulation )may have a variable amount of angioma mixed in with them; if this is marked they are called glomangiomas. The purer form mostly involves the extremities and are extremely tender.

Eosinophils

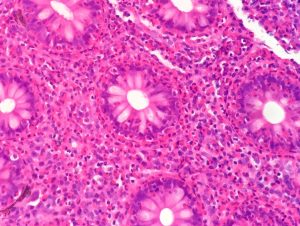
This post was stimulated by a case of eosinophilic colitis I reviewed at an MDT this morning. The images are below.

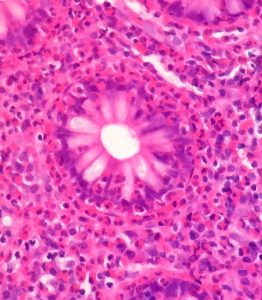
They show sheets of eosinophils in the lamina propria and infiltrating crypts. They are easily recognised by their bilobed nuclei and prominent red granules.


This was an opportunity to review eosinophils.

Eosinophils are conspicuous in inflammatory reactions triggered by IgE, such as asthma, and by parasites and are increased by TH-2 activation.  IL-5 and GM-CSF increase the production of eosinophils by the bone marrow. They are associated are recruited into the tissue by eotaxins which are CC chemokines.

Eosinophils have 2 types of effector function:

  1. they release toxic granule proteins  (e.g. major basic protein which is toxic to parasites) and free radicals.
  2. they synthesise prostaglandins, leukotrienes and cytokines.

In the context of this case, likely causes include gut parasites, such as schistosomiasis, and allergic reactions to drugs.

If you want to read more try the excellent British Society of Immunology Website: https://www.immunology.org/public-information/bitesized-immunology/cells/eosinophils