Author: Austen El-Osta

We have counted loneliness. Now we need to change it.

Our new research examines loneliness and social capital in more than 135,000 adults. The challenge now is to turn those findings into better questions – and interventions worth investing in.

A loneliness score can tell us something important about someone’s life, but it cannot tell us what would make that life less lonely. That gap is where I believe the next chapter of loneliness research belongs. In our new paper in BMC Global and Public Health, we analysed data from 135,725 adults participating in the INTERACT study in England. We examined factors associated with loneliness using two established measures, alongside a separate analysis of social capital: people’s perceptions of neighbourhood trust, cohesion and reciprocity.

Among respondents, younger age, being single, unemployment and disability were consistently associated with greater loneliness. Larger friendship networks were associated with lower loneliness. Older, married and retired respondents more frequently reported high social capital, while people with disability or long-term conditions had lower adjusted odds of reporting it. These findings give us questions to pursue but they do not give us a ready-made intervention.

That distinction should shape everything we do next. The study used a volunteer sample and measured people’s circumstances at one point in time. It cannot establish what causes loneliness, estimate how common it is across England, or tell us which intervention would work. A large sample does not remove those limitations.

For me, this is the starting point for a more demanding research agenda: what would we actually change, for whom, and how would we know it helped? Consider the association between friendship networks and loneliness. It would be tempting to translate it into a simple instruction: help people make more friends. But an association cannot tell us whether expanding someone’s network will reduce their loneliness, whether loneliness makes relationships harder to sustain, or how other circumstances influence both. “More friends” is also an outcome to aspire to, rather than a sufficiently specified intervention. Who makes the introduction? Where does the first meeting happen? What helps someone return? What makes an encounter develop into a relationship that matters? Those are intervention-development questions. They deserve the same intellectual attention as the statistical models that bring them into view.

Imagine, as a design exercise, a community programme offering weekly group activities. Before commissioning it, I would want to ask what problem it is intended to address. A shortage of opportunities to meet people? Difficulty entering unfamiliar social settings? The loss of a close relationship? Practical barriers to leaving home?

Each answer points towards a different proposition to test. For someone who wants to attend but cannot reach the venue, transport support could be a candidate component. For someone apprehensive about arriving alone, a familiar person accompanying them might be worth testing. For someone seeking a close, dependable relationship, attendance at a large group may be the wrong primary outcome. These are hypotheses, not findings from our study… but their value lies in making the proposed route to benefit explicit – and therefore open to challenge!

Social capital adds another set of questions. Our paper examined it as a separate outcome; it did not establish that increasing neighbourhood trust reduces loneliness. Nevertheless, I would argue that intervention development should ask what happens beyond the individual referral. What kind of community is someone being invited into? Who feels welcome there? Can participants influence what happens? Are there opportunities to contribute as well as receive support? What resources would a local organisation need to sustain relationships beyond a short funding period?

I want self-care to sit within that discussion. Any call for people to strengthen their own social connections should be accompanied by serious questions about the opportunities and support available to them. “Take action” is an incomplete offer unless we also examine what makes action possible.

The next step should be a programme of co-designed, explicitly testable interventions. People experiencing loneliness should help define the problem, choose outcomes that matter and identify features that make participation acceptable. Their involvement should extend to interpreting why an approach succeeds, disappoints or reaches only some of its intended participants. Evaluation then needs to follow the whole journey.

Counting invitations, referrals and attendance can describe delivery. To establish benefit, we need to examine changes in loneliness and wellbeing, whether those changes last, and how outcomes compare with what would have happened without the intervention. Randomised evaluations should be used where feasible, with credible alternatives where they are not. We should also examine who never takes up the offer, who leaves, and whose circumstances make participation difficult. I would want a commissioner to see those findings alongside the average outcome and the cost. An intervention’s reach is part of its practical value.

Our study also offers a reason to think carefully about measurement. Educational attainment showed different associations depending on which loneliness measure we used. That finding cautions against treating different instruments as interchangeable. Future evaluations should specify what they seek to change and combine appropriate measures with accounts of participants’ experiences.

None of this requires abandoning observational research. It requires giving its findings a purposeful next step.

For the Prevention Lab, my challenge is to researchers, funders and commissioners alike: make room for the difficult work between identifying a pattern and delivering a useful intervention. Fund development, refinement and rigorous evaluation. Specify the benefit being sought. Be willing to adapt or stop an approach when the evidence disappoints.

I want the next paper to answer a harder question: what did we change, who benefited, and was the difference worth sustaining? The people behind our data deserve that next chapter – and a meaningful role in writing it. Through our ongoing qualitative research, we are exploring personal stories and journeys to understand what connection, belonging and support mean in everyday life. These accounts will inform the co-production of interventions grounded in people’s experiences, ready to be tested for the difference they make to their lives.


The Future of Self-Care: Emerging technologies, public trust & personal autonomy

Who should be in control when technology becomes part of how we look after ourselves? That question belongs at the centre of the digital self-care agenda. In my view, emerging technologies should be judged by the understanding and practical capability people gain, and by the control they retain over decisions affecting their lives.

The World Health Organization’s account of self-care includes maintaining health and coping with illness, with or without professional support. For me, the purpose of innovation is to make those activities more manageable within the realities of people’s lives.

Emerging technologies offer different ways to access information and assistance. Virtual reality (VR) creates an immersive digital environment; augmented reality (AR) adds digital information to a view of the physical world. Smart glasses offer functions that vary by device, including cameras, audio and, in some models, visual displays. Brain–computer interfaces (BCIs) translate brain signals into commands for external devices. Because their mechanisms and risks differ, each needs evaluation suited to its purpose.

Starting with the self-carer’s goals

My starting point is the self-carer’s goal. They may want an explanation they can understand, support with a difficult task or a way to communicate their needs. The design question is whether a particular technology helps them pursue that goal, under conditions they find acceptable. Our work on Self-Driven Healthcare proposed connecting people’s own health information and monitoring tools with professional care. That vision depends on accessible support and integration with health services, with people able to influence decisions about their care.

Our BMJ Open study of spatial computing in health and self-care explored these issues with UK adults, including healthcare professionals. Respondents identified possible value for self-care and patient education alongside barriers involving cost, training and privacy. These findings reflect perceptions rather than evidence of clinical benefit.

Smart glasses illustrate both the promise and the open questions. Be My Eyes connects blind and low-vision users of supported Meta glasses with sighted volunteers who can view the camera feed and provide spoken assistance. Its value, however, should be assessed against users’ goals and the alternatives available to them. This is why we launched the SMART EYES study to examine public views on AI-enabled smart glasses, including privacy, accessibility and possible support for health and self-care. To be meaningful, evaluations must start with people’s experiences, concerns and expectations. They should also account for the time needed to learn a tool, maintain it and resolve problems. The practical test is whether the overall experience becomes easier for the person using it.

In an earlier Prevention Lab article on health literacy, I argued that people need to understand information, judge its relevance and decide what to do next. Digital assistance should support those capabilities. Our UK symptom-checker survey found that respondents wanted help understanding symptoms and deciding whether to seek care, alongside concerns about privacy and losing face-to-face consultations. At the same time, our 2023 systematic review of symptom checkers found variable diagnostic and triage accuracy in the studies available at that time.

Earning public trust

Public trust also needs to be framed with care. SCARU’s RADIANT Voices research on AI and software as a medical device (SaMD) examined trust in clinical decision-making. We found higher trust in AI-assisted decisions than in AI-only decisions, alongside strong support for disclosure and professional oversight. These findings describe preferences, not evidence of safety or effectiveness.

Trust in individual pieces of advice matters as well. Our Trust in AI-Generated Health Advice (TAIGHA) scale and its four-item short form, TAIGHA-S, focus on trust in a specific piece of advice. Initially validated with 385 UK adults in a symptom-assessment scenario, they measure trust and distrust as related but distinct dimensions.

Our PLOS Digital Health study of community perspectives on BCIs likewise found concerns about implantation risks and cost, with participants emphasising regulation and public education. Those concerns belong in the decisions that set research priorities. Public engagement should give people a meaningful opportunity to influence development, including the option to question whether an application is desirable.

Because public trust has to be earned through evidence and accountability, developers and health services should explain the evidence for a proposed use, its limitations and who is accountable when something goes wrong. People should also have a practical way to challenge advice or report harm. The WHO’s guidance on generative AI in health supports clear tasks, appropriate accuracy and reliability, and involvement of patients and other affected groups in development.

Regulation and intended purpose

SaMD refers to software intended to perform a medical purpose without being part of a hardware medical device. Its increasing pervasiveness makes the intended purpose especially important. The MHRA’s guidance emphasises specifying that purpose and matching it to supporting evidence. Whether an application is accessed through a phone, headset or glasses, assessment should address its intended users, clinical function and setting. Determining regulatory status therefore requires attention to the specific features and claims of health-related software.

The developer’s experience deserves attention too. Our study of medical-software developers’ experiences of regulation, available as a preprint, describes participants’ difficulties obtaining reliable advice and navigating requirements. Clear guidance, accessible expertise and proportionate evidence requirements should form part of responsible innovation.

Autonomy in everyday use

Personal autonomy also needs to be built into everyday use. Who chooses the goal behind a reminder or recommendation? Who can change it? People should understand the purpose of the support they receive and be able to pause or decline it. Commercial interests should be visible, especially where advice is connected to the sale of a product or service. Delegating a task should leave the individual able to influence the terms of that delegation.

For smart glasses, autonomy also concerns the relationship between the wearer and people nearby. Using a camera to assist with a task, retaining a recording and sharing it are distinct activities. Each deserves a clear explanation and an appropriate decision about permission.

That discussion should also respect the dignity of people using assistive technology. Someone should not have to disclose a diagnosis to justify their device to a stranger. Equally, the people around them should have meaningful ways to understand and influence what happens to their information. Good safeguards need to address both concerns in practice.

Equity and shared responsibility

Equitable access should be considered from the outset and meaningful evaluations need to address affordability, language, disability-related requirements and the support needed to use a technology. People should retain an accessible route to care if a device is unsuitable or they choose not to use it. A service should also plan for interruptions, software changes and the point at which a product is no longer supported.

Health systems and wider society retain responsibilities of their own. A self-care strategy needs accessible professional advice and practical support, alongside attention to housing, working conditions and other constraints on daily choices. Digital tools should be assessed within that context and should not become a justification for transferring responsibilities to people without considering the resources available to them.

Evaluating what matters

For researchers and commissioners, this calls for evaluation beyond stated willingness to adopt a product. Relevant outcomes include understanding, appropriate action, wellbeing and harms, with results examined across different groups. We should measure the work expected of users and carers, compare realistic alternatives and study use over time. A successful demonstration is only the starting point for that work. Ultimately, the future of self-care must be shaped with the people expected to use these technologies. They should help define the problems worth solving, the evidence that matters and the boundaries they want respected. The measure of progress should be whether people have more meaningful choices, stronger capabilities and dependable support in looking after their health. These principles guide our work in practice. Through our patient and public involvement and engagement PPIE activities, self-carers regularly share their feedback with us, and their insights shape our projects. Their perspectives keep our research grounded in the realities of looking after one’s health, and we are grateful for the time and candour they bring. We will continue to build our work with them, rather than for them.

Building the future together

In my next blog, I will reflect on the importance of PPIE and adopting a team science approach in driving our work, and on what bringing together lived experience and diverse expertise contributes to research on self-care.

A home for the science of self-care: launching the International Academy for Self-Care Research

Bangkok, 10 September 2026

Self-care is everywhere. It is present in the decisions people make each morning about what to eat, how to move, when to rest and how to manage their health. It is present when somebody recognises a symptom, takes a medicine, monitors a long-term condition, seeks advice from a pharmacist, uses a digital health tool, supports a family member, or decides that professional care is needed. It is also increasingly visible in health policy. Yet something important has been missing: an academic home devoted specifically to the science of self-care.

Today in Bangkok, we are taking a significant step towards changing that with the launch of the International Academy of Self-Care Research (IASCR).

IASCR was conceived as an independent academic institution dedicated to defining and advancing self-care as a distinct field of scientific enquiry. Its purpose is not to promote a particular intervention, profession, product or model of healthcare. It is to strengthen the scientific foundations upon which our understanding of self-care rests.

The launch of the International Academy of Self-Care Research (IASCR), Bangkok, Thailand, 10 September 2026. IASCR was established to provide a global academic home for the development of self-care as a distinct field of scientific enquiry.

Why does self-care need an Academy?

Self-care has an unusual problem. Its importance is widely acknowledged, but its evidence base remains dispersed. Researchers studying medication use may rarely interact with researchers studying health literacy. Digital self-management may sit in one literature, informal caregiving in another, lifestyle behaviours somewhere else, and traditional or complementary approaches in yet another. Public health, primary care, behavioural science, nursing, pharmacy, psychology, sociology, digital health and health economics can all be examining parts of the same phenomenon without necessarily recognising that they are contributing to a common field. The result is an evidence landscape that remains fragmented across disciplines, inconsistently defined and comparatively poorly supported by dedicated research infrastructure.

That fragmentation matters. Without common concepts, measures and methodological standards, it becomes difficult to accumulate knowledge across studies. Without stronger research networks, we repeatedly answer small parts of large questions. And without a clearly identifiable scientific field, self-care risks remaining peripheral to mainstream research funding even while governments and health systems increasingly expect individuals, families and communities to assume greater responsibility for maintaining health.  IASCR has been created to address this structural gap.

Self-care as a field of enquiry

One of the founding propositions of the Academy is deceptively simple: Self-care should be studied in its own right. Too often, self-care appears in research as an adjunct to something else: adherence to a clinical intervention, management of a particular disease, uptake of a digital technology, or modification of a specific behaviour.  Those are important questions, but they do not capture the whole phenomenon.

Self-care unfolds across the life course. It is shaped by capability, confidence, culture, family, community, commercial environments, technology, inequality, access to information and access to professional care. It may involve prevention, health maintenance, symptom recognition, self-management, self-medication, rehabilitation and decisions about when not to self-manage.

“The ambition is not simply to conduct more studies about self-care. It is to develop the science of self-care”

The founding documents of IASCR therefore deliberately position self-care as a complex phenomenon requiring behavioural, social, cultural, digital, traditional and equity-focused approaches.  That distinction is important. The ambition is not simply to conduct more studies about self-care. It is to develop the science of self-care.

What should that science look like?

IASCR’s emerging research agenda begins with some fundamental questions. What exactly constitutes self-care? Where are its conceptual boundaries? How should self-care capability, behaviour and outcomes be measured? Which aspects are universal, and which are culturally or contextually specific? How do poverty, education, gender, ageing, multimorbidity and digital exclusion alter people’s capacity to care for themselves? Where does responsible self-care end and professional healthcare need to begin? How are artificial intelligence, wearables, diagnostics and other technologies changing that boundary? And perhaps most importantly: who benefits from contemporary models of self-care, and who risks being left behind? These are no longer peripheral questions. They sit at the intersection of prevention, health-system sustainability, population ageing, digital transformation and health equity.

Building infrastructure, not simply another organisation

The Academy’s proposed programme therefore extends beyond conventional networking. Its remit includes identifying global research priorities and evidence gaps; developing conceptual and methodological tools; supporting early- and mid-career researchers; convening interdisciplinary research communities; encouraging high standards of transparent and reproducible research; and translating robust evidence responsibly into policy, practice and public understanding. Among the activities envisaged are a Global Self-Care Research Observatory, an annual international research forum, open-access research tools and resources, methodological guidance, thematic reviews, international capacity-building activities and collaborative multi-country research programmes.

There is also an explicit commitment to global representation. The Academy’s framework recognises that a credible science of self-care cannot simply export assumptions generated in high-income settings to the rest of the world. Participation across regions, disciplines, cultures and lived experiences — including stronger representation from low- and middle-income countries — is therefore intended to be built into its development.

Why Bangkok matters

It feels appropriate that this next chapter begins in Bangkok. The Academy is being launched alongside colleagues working across Thailand, ASEAN, Australia, Canada, China, Brazil and the United Kingdom, bringing together perspectives on self-care that emerge from very different health systems and cultural contexts. The programme surrounding the launch deliberately moves between the global and the local: from the international state of self-care to healthy ageing, national public-health strategy, urban communities and the future of self-care within Thai society. That is precisely the intellectual territory that IASCR must occupy. A global science of self-care cannot be constructed from a single healthcare system, profession or worldview.

The next phase

Launching an Academy is the easy part. Building a field is harder. It requires researchers willing to cross disciplinary boundaries. It requires funders prepared to support questions that do not fit neatly within traditional disease silos. It requires methodological development, international datasets, stronger theory, reproducibility, genuine engagement with communities and much greater investment in research capacity.  It also requires intellectual humility. Some of the most important questions ab out self-care remain unanswered — and some have not yet been adequately formulated.

IASCR therefore begins not with the claim that the field is complete, but with the recognition that considerable scientific work remains to be done. Its founding purpose captures the ambition succinctly: to define, strengthen and coordinate self-care research globally, while building the conceptual coherence, methodological development, visibility and international collaboration needed for cumulative science.

A new academic home

For decades, self-care has existed simultaneously everywhere and nowhere in academia: embedded across countless disciplines but rarely possessing an institutional centre of gravity of its own. Today we begin to create one. The International Academy of Self-Care Research represents a proposition that we believe is increasingly difficult to ignore: Self-care is too important to health, society and the future of healthcare to remain scientifically fragmented.

If prevention is to move upstream, if people are to be meaningfully empowered rather than simply handed greater responsibility, and if health systems increasingly depend upon what happens outside clinics and hospitals, then we need a much deeper understanding of the science that underpins those activities. That is the work ahead.

And today, in Bangkok, that work acquires a new home.

Health Literacy is the Operating System of Self-Care

Imagine receiving a blood pressure monitor without understanding the readings. A medicine without clear instructions. Or advice to “live more healthily” without knowing where to begin.

These examples raise a question that should sit at the centre of prevention: what does someone need to turn health information into a decision they can use?

Every year, on International Literacy Day celebrated the world over on 8 September, is an opportunity to reinforce health literacy as the operating system of self-care: the capability that helps people interpret information, judge its relevance and decide what to do next.

What is health literacy? 

WHO describes health literacy as the ability to find, understand, critically assess and use health information and services. It also recognises that these abilities depend on how organisations communicate and what resources people can access. Health literacy therefore involves both individual capability and the conditions in which people make decisions.

The operating system metaphor helps explain why this matters. We can think of self-care practices – taking medicines, preparing food, being physically active or monitoring symptoms -as applications. Health literacy helps connect those activities to understanding: Why am I doing this? What should I expect? How do I know whether it is helping? When should I seek support?

WHO also explicitly identifies health literacy as a foundation for people’s active participation in their own health. Its account of self-care includes everyday health practices and the use of medicines, devices and tests, within an environment that provides appropriate support and access to professional care.

This has an important implication for how we judge successful self-care. We should indeed value someone recognising their limits and asking for help just as much as their ability to manage independently. A useful question for any self-care intervention is whether people understand both what they can do themselves and when they need someone else.

Consider a hypothetical heatwave. A person might understand the advice to keep their home cool yet have little control over an overheated rented flat. They might know they should reduce exertion but work outdoors. They might recognise concerning symptoms yet be uncertain where to seek advice. We should distinguish these problems. Understanding, practical opportunity and access to support each deserve attention. A leaflet cannot change a tenancy agreement or a working condition

Delimiting self-care

That is also where the operating system metaphor reaches its limit. People need resources, relationships and services alongside knowledge. Any prevention strategy built around self-care should ask what makes the recommended action feasible.

There is a corresponding responsibility for organisations. WHO emphasises that health literacy is shaped by social conditions and that information providers should make trustworthy information understandable and actionable.

For the Prevention Lab, I would translate this into a practical design principle: every recommendation should come with a usable route to action. “Be more active” should open a conversation about an achievable starting point. A monitoring device should come with an explanation of its readings and a clear route to advice. A digital service should make it easy to find help when its instructions are unclear. We should also make room for critical judgement. When someone encounters a compelling health claim, useful questions include: Who produced it? What evidence supports it? What are they selling? What remains uncertain? Does this apply to my circumstances?

It is arguable that asking these questions is itself a form of self-care and our evaluation methods should reflect that ambition. Alongside counting views, downloads or leaflets distributed, we should examine whether people can explain the next step, assess a claim, use a tool appropriately and obtain support. We should ask whose needs the intervention meets and who still faces barriers.

Evey year, International Literacy Day offers an opportunity to put these questions into the prevention agenda. The proposal is simple: treat health literacy as a core requirement whenever we ask people to take an active role in their health. And given that health literacy is the operating system of self-care, building it belongs in the design of every self-care intervention.

PRE-ACT: From prediction to prevention & making risk intelligence actionable in primary care

Health systems are becoming increasingly good at predicting risk. Routinely collected health data, machine learning, clinical risk scores, remote monitoring and digital technologies can identify people who may be at increased risk of disease or adverse health outcomes – sometimes well before those outcomes occur.

But prediction is not prevention.

Knowing that someone is at increased risk only creates value if that information can be translated into an appropriate response: something understandable to the person, clinically meaningful to professionals, feasible within routine care, and capable of supporting action. This is the problem that the Prediction-Enabled Action for Self-care in Primary Care (PRE-ACT) consortium sets out to address.

The PRE-ACT consortium is a collaboration between Imperial College London Self-Care Academic Research Unit (SCARU) and the Research Unit OPEN, University of Southern Denmark, bringing together researchers, clinicians and implementation partners with expertise spanning primary care, public health, risk prediction, digital health, behavioural science and self-care.

Closing the gap between risk and action

Much of the innovation in predictive healthcare has understandably concentrated on improving model performance: identifying the right variables, improving discrimination and calibration, and determining whether an algorithm can accurately classify risk. These are necessary questions. But they are not sufficient:

Between a risk estimate and an improved health outcome lies an important translational pathway. Risk must be interpreted. It must be communicated appropriately. Decisions need to follow. Patients may need support to act. Primary care teams need workable pathways through which to respond. And all of this must occur without widening existing inequalities.

PRE-ACT starts from the proposition that prediction should be viewed as the beginning of a preventive pathway, rather than its endpoint.

The initiative therefore brings together predictive analytics, decision support, primary care and self-care within a single translational framework. Its focus is not simply on whether we can identify risk, but on what should happen next.

Why self-care matters

This question is particularly important as healthcare moves towards earlier intervention and greater participation by patients in managing their own health.

The 2018 Declaration of Astana on Primary Health Care provides an important foundation. It renewed the global commitment to primary health care as a route to universal health coverage and emphasised, among other principles, the importance of prevention and health promotion, empowering individuals and communities, and enabling people to acquire the knowledge, skills and resources required to maintain their health.

PRE-ACT takes this principle into an increasingly data-driven healthcare environment. If predictive technologies can identify an opportunity to prevent deterioration, then we should also ask how individuals can be meaningfully supported to respond. That may involve self-monitoring, behavioural change, appropriate use of digital tools, supported self-management, or timely engagement with healthcare services.

Self-care in this context does not mean shifting responsibility from health systems to individuals. It means designing systems in which people are equipped and supported to participate in prevention, with appropriate professional oversight and clear routes into care.


Prediction-enabled prevention must also be responsible

There are important safeguards. A technically sophisticated predictive system may still have limited value if clinicians cannot interpret its output, patients do not understand what the result means, actionable services are unavailable, or those with lower digital access are systematically disadvantaged. PRE-ACT therefore places issues such as equity, human oversight, transparency, evidence, privacy, clinical governance and implementation readiness alongside predictive performance.

These considerations matter because the future of prevention will increasingly involve interactions between people, professionals, health systems and intelligent technologies. Success cannot be judged solely by the accuracy of an algorithm. We also need to ask whether an intervention is understandable, actionable, acceptable, equitable and capable of being integrated into real-world care.

From predicting risk to changing outcomes

One way of expressing the PRE-ACT pathway is: Prediction → Interpretation → Decision support → Activation → Self-care & clinical action → Outcomes

Each transition matters. A failure at any point can break the chain between recognising risk and preventing harm. Conversely, designing these elements together creates an opportunity to move predictive technologies away from passive risk stratification and towards genuinely preventive healthcare. This is the broader ambition of PRE-ACT: to help define what responsible, human-centred and actionable prediction should look like in primary care.

As predictive technologies become more powerful, the central question may therefore become less “How accurately can we predict what happens next?” and more: “What can we enable people and health systems to do differently because we know?” That is the point at which prediction becomes prevention.

From Measuring Loneliness to Preventing It

Loneliness is usually experienced as something intensely personal. Public health, however, has to ask a broader question: What if loneliness is shaped not only by individuals, but also by the places, relationships and systems surrounding them?

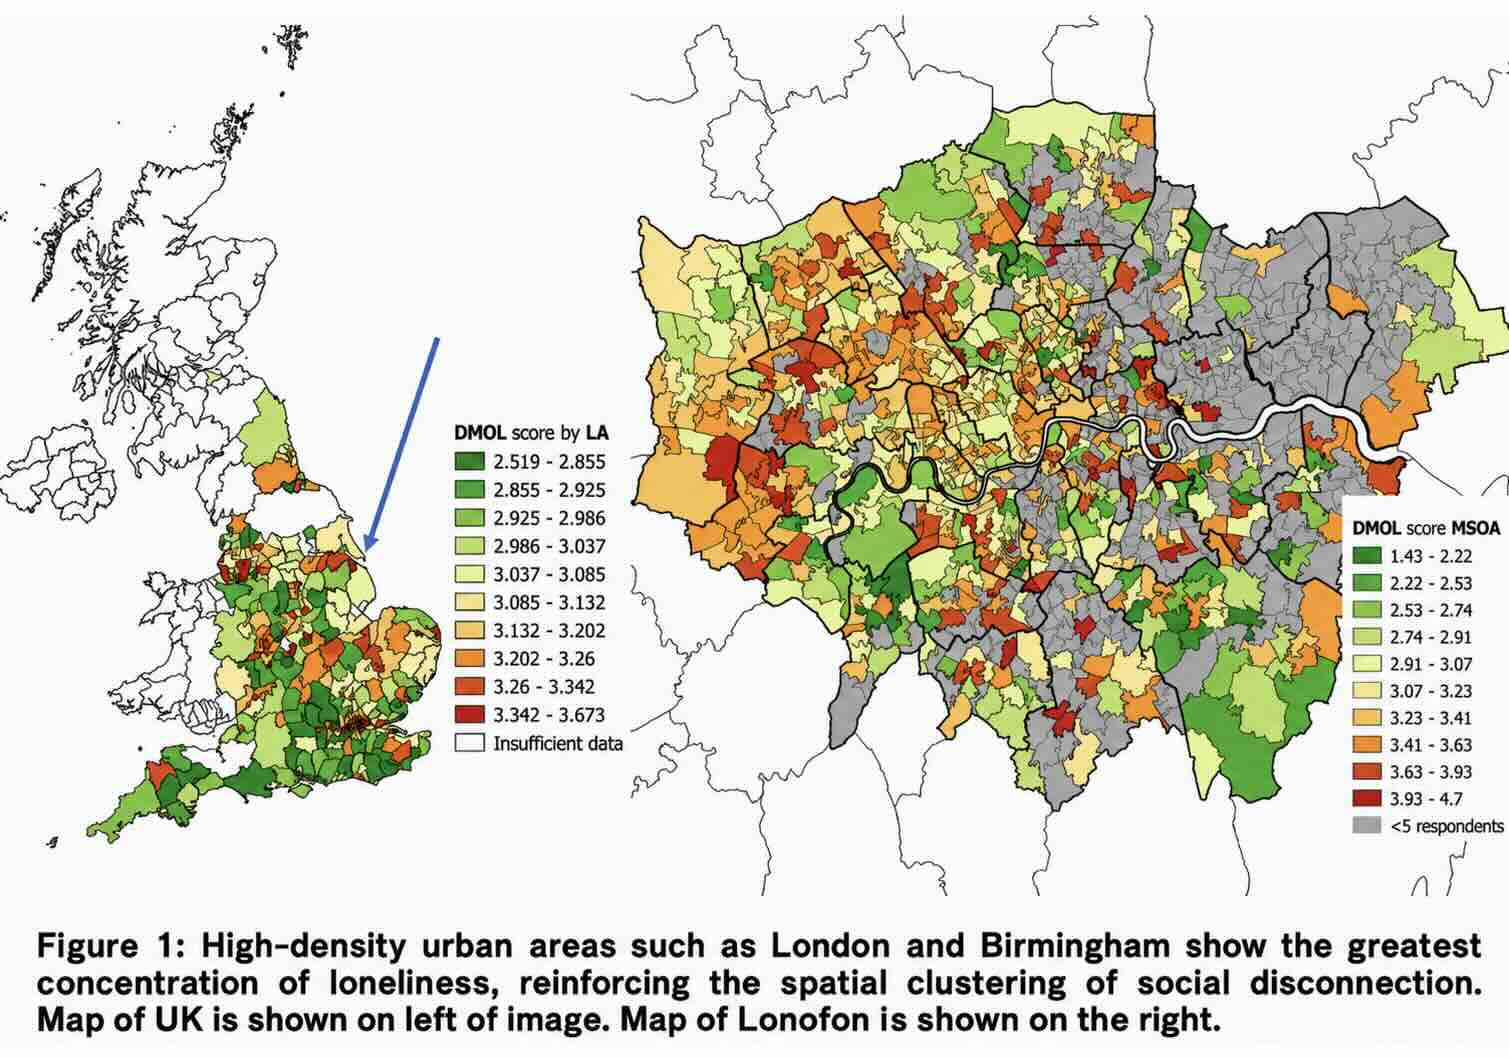
The first published paper in a series to report the findings of the Measuring Loneliness in England (INTERACT) Study, led by Imperial College London’s Self-Care Academic Research Unit (SCARU), provides an important starting point. More than 135,000 adults aged 16 and over participated. Among them, 16.5% reported feeling lonely “often or always”, while around one in five frequently reported lacking companionship, feeling left out or feeling isolated from others.

These findings are striking, but they require careful interpretation. INTERACT recruited a volunteer, non-probability sample, so the results describe the people who participated rather than providing a precise estimate of loneliness prevalence across England.

Its particular value lies elsewhere: in combining scale with geographical and social detail. INTERACT examines loneliness alongside social connection, neighbourhood trust, cohesion, health and socioeconomic circumstances. By linking responses anonymously to geographical areas, we can begin to move beyond asking simply: “How many people are lonely?” towards: “Where does loneliness appear to concentrate, among whom, and within what social and neighbourhood contexts?” For prevention, that distinction matters.

A map is not an intervention

Mapping loneliness can help identify patterns and generate hypotheses. But describing a problem is not the same as changing it. The real challenge is how evidence can inform decisions about where attention is needed, which community assets already exist, where gaps remain and which approaches should be tested. That is why SCARU has been working closely with the public-health teams serving Westminster and Kensington and Chelsea, alongside voluntary and community organisations, health partners and local networks. The aim is not simply to collect data about communities, but to develop research with the organisations and people who understand them.

Westminster’s Building a more connected Westminster Loneliness Action Plan creates an important opportunity to take this further. Rather than treating loneliness as the responsibility of a single service, the Action Plan seeks to bring together public services, communities and local organisations in a more coordinated response.

From INTERACT to LAP-IMPACT

This creates the next scientific question: Can a coordinated, place-based approach actually reduce loneliness and strengthen social connection? That is the thinking behind LAP-IMPACT, the research programme we are developing with our local partners. Subject to competitive funding, governance and the necessary approvals, the aim would be to move from mapping loneliness towards rigorously evaluating the response. The questions are practical and important. Who does a Loneliness Action Plan reach? Which components appear most promising? Are benefits distributed equitably? How does implementation vary between neighbourhoods and organisations? What role do community assets play? And what can other local authorities learn from the experience? These questions matter because an Action Plan should not be judged simply by whether activities happened. The more important question is whether the local system changed in ways that were meaningful for residents.

Prevention is not telling people to be less lonely

There is also a danger in framing loneliness only as an individual problem. Advice such as joining a group, volunteering or taking part in community activities may help some people. But it can obscure a more fundamental issue: Were meaningful opportunities for connection accessible in the first place?

A person cannot participate in an activity they cannot reach. Signposting has limited value if services have no capacity. Community assets cannot fulfil their potential if they remain disconnected from wider local systems.  This is why loneliness prevention must include the infrastructure of connection: the services, organisations, neighbourhood assets and relationships that make social participation possible. For SCARU, this also reflects a broader principle of self-care research. People exercise agency within environments that can either expand or constrain their options. Social wellbeing is no different.

From knowing where loneliness is to knowing what works

INTERACT has given us an unusually large window into loneliness and social connection in England. The next question is what we do with that knowledge.

Can local intelligence help communities organise prevention differently? Can services become better connected? Can existing community assets be strengthened? Can people be reached before loneliness becomes entrenched? And can we demonstrate which approaches work, for whom and under what conditions?

That is where loneliness research now needs to go. The INTERACT Study helps us understand the landscape. LAP-IMPACT is about understanding how that landscape might be changed. That is the Prevention Lab model in practice: moving from evidence, to action, to evaluation.

When Does Prevention Become Medicine? Trust, legitimacy & the future of lifestyle medicine

At what point does something we do every day become medicine? Eating. Moving. Sleeping. Managing stress. Connecting with other people are among the most ordinary acts of human life. They happen largely beyond hospitals, clinics and consultation rooms. Yet they are also intimately connected with health.

And therein lies an intriguing tension: we readily accept that medicines prescribed for hypertension, diabetes or depression belong within healthcare. But what happens when the therapeutic proposition is not principally a tablet, procedure or device, but a different way of living? Who should deliver that intervention? What qualifications should they possess? Who do people trust? And perhaps most importantly: what makes an approach feel sufficiently legitimate to belong within medicine at all? These questions sit at the heart of our recently published study in BMJ Open, Legitimacy, trust and readiness for implementing lifestyle medicine in England.

The paradox of the unfamiliar familiar

One of the most striking findings was a paradox; most people were not particularly familiar with the term lifestyle medicine. Among 733 participants, only 26% of the overall sample had previously heard of it. Among healthcare professionals, awareness was considerably higher, at 62%. And yet, when we moved beyond the label, people largely recognised its substance. Nutrition. Physical activity. Sleep. Stress management. These were readily understood as legitimate components of health. In other words, lifestyle medicine appears to suffer from an unusual problem: its constituent ideas may be more familiar than the discipline that brings them together.

This matters, because public health frequently assumes that if an intervention is evidence-informed, useful and available, people will engage with it. But healthcare does not operate through evidence alone. It also operates through meaning, expectation, professional authority and trust. Before a person asks, “Does this work?”, another question may already be operating beneath the surface: “Is this really medicine?”

Legitimacy is not an abstract concept

Our findings suggest that this question has practical consequences. Perceived legitimacy was strongly associated with participants’ stated intention to use a lifestyle medicine service delivered through the NHS. Nearly half of participants said they would use such a service if it were available through the NHS, rising to around two-thirds of healthcare professionals. Because the study was cross-sectional, we cannot conclude that perceiving lifestyle medicine as legitimate causes people to use it. But the association raises an important implementation question. Perhaps prevention cannot simply be offered, but must instead also be socially and institutionally authorised.

That distinction is more important than it first appears. The same advice (eat differently, move more, sleep better, reduce harmful exposures, strengthen social connection) can be interpreted very differently depending on who gives it, where it is given and the institutional framework surrounding it.

Advice from a friend is advice. Advice from an influencer is content. Advice from a clinician may be interpreted as healthcare. The behaviour being discussed may be identical, but meaning attached to it is not.

Trust follows more than knowledge

Our findings make this particularly visible. Participants reported high levels of trust in lifestyle advice delivered by clinicians who had formal lifestyle medicine training: 73% expressed high trust. Trust was substantially lower for non-medical professionals, at 42%, even when those professionals possessed lifestyle medicine qualifications. This presents a difficult but important question for prevention.

What exactly are people trusting?

Is it knowledge? Credentials? Professional regulation?  Clinical accountability? The symbolic authority of medicine? Or some combination of all four? There is no simple answer in our data. Nor should these findings be interpreted as evidence that one professional group necessarily provides better lifestyle support than another. But they reveal something that implementation science cannot afford to ignore: the credibility of an intervention and the credibility of its messenger may be inseparable in the minds of those being asked to act upon it.

For lifestyle medicine to scale, therefore, the challenge is not merely to identify effective interventions. It is to develop trusted systems through which those interventions can be delivered.

The prevention paradox inside healthcare

There was another tension in the findings in that healthcare professionals appeared interested in lifestyle medicine, yet the infrastructure surrounding them appeared much less mature.

Among the 58 healthcare professionals surveyed, 48% reported providing lifestyle-related advice to patients, while only 21% reported having received formal training in lifestyle medicine. Almost two-thirds wanted additional training or resources. The principal barriers they identified included patient readiness, limited time and insufficient training. Most strikingly, only 3% thought that the NHS currently supported lifestyle-based approaches “very well”. Because the healthcare professional subgroup was small, these estimates require appropriate caution, but they do generate questions that require further investigation.

We increasingly ask healthcare professionals to practise prevention while maintaining systems historically structured around the identification, treatment and management of established disease. We tell clinicians that lifestyle matters and encourage conversations about physical activity, food, sleep, stress and social connection. But if those conversations are to become a meaningful part of healthcare rather than an optional addition to it, clinicians also require time, competencies, referral pathways, professional standards and services to which patients can actually be directed. A health system cannot become preventive simply by asking its workforce to talk more about prevention. Prevention needs infrastructure.

Perhaps the question is larger than lifestyle medicine

This is where our study findings lead to a broader philosophical question. Modern medicine has become extraordinarily sophisticated at intervening once pathology is visible. We can image increasingly subtle abnormalities, quantify biological risk, stratify populations algorithmically and develop treatments targeted at increasingly specific molecular pathways. Yet many of the actions through which health is created or lost remain remarkably ordinary. They happen in supermarkets and kitchens, on pavements and playing fields, in workplaces and bedrooms, within families, friendships and communities. The future of prevention may therefore depend partly on whether healthcare can become more comfortable operating at the boundary between the clinical and the everyday.

Lifestyle medicine occupies precisely this boundary. Its proposition is not that ordinary life should become medicalised. Nor should structural determinants of health be reduced to individual responsibility. People do not make choices in a vacuum: income, housing, work, neighbourhoods, commercial environments, education and opportunity all constrain what is realistically possible. The more interesting proposition is that healthcare might take the conditions of everyday life more seriously without pretending that every determinant of health belongs inside the consultation room. That requires a different conception of prevention. Not prevention as instruction. Not prevention as telling people to “make better choices”.

But prevention as capability: that is, creating the knowledge, confidence, opportunities, professional support and environments that make healthier lives more achievable.

From lifestyle advice to prevention infrastructure

For that reason, the future of lifestyle medicine may depend less on defending the term and more on answering three practical questions: Can people trust it? Can professionals deliver it competently? Can health systems support it consistently and equitably?

Our findings suggest that these domains (legitimacy, capability and system readiness) are deeply interconnected. Awareness alone will not be enough. Enthusiasm alone will not be enough. Nor will simply adding another service to an already crowded healthcare landscape.

Training matters. Standards matter. Professional credibility matters. Institutional endorsement matters and implementation matters. There is also an important warning here for those of us interested in prevention and self-care. If lifestyle medicine becomes available primarily to people who already possess the resources, knowledge, confidence and time required to engage with it, it could reproduce rather than reduce existing inequalities. A credible model of lifestyle medicine must therefore be more than clinically plausible. It must also be accessible, trusted and equitable.

So when does prevention become medicine?

Perhaps there is no single moment… Perhaps prevention becomes medicine only when scientific evidence is translated into competent practice; when people trust the person delivering it; when health systems make room for it; and when individuals are given meaningful opportunities to participate in decisions about their own health.

The distinction between treatment and prevention may ultimately be less rigid than our institutions have made it appear.

After all, health is not produced only when we enter the healthcare system. It is being shaped long before we arrive. The challenge for the NHS and for health systems more broadly is therefore not simply to treat disease earlier. It is to decide how far upstream healthcare is prepared to travel. Lifestyle medicine offers one possible route.

Our study suggests that people may be more receptive to that journey than familiarity with the terminology alone would suggest. But for lifestyle medicine to move from an appealing idea to a credible component of prevention, it will have to earn something that cannot be manufactured through branding alone: trust.

And perhaps that is the larger lesson. The future of prevention will not be determined only by what we know can improve health. It will also depend on whether we can build institutions, professions and systems that people believe have the legitimacy to help them act on that knowledge.


International Self-Care Day 2026: Advancing the Public Health Legacy of Self-Care

Every year, International Self-Care Day is marked on 24 July. The date (24/7) is a deliberate reminder that self-care is not confined to occasional acts of wellbeing, but is practised continuously: in the decisions people make about food, physical activity, sleep, medicines, relationships, symptoms, risk and when to seek professional support.

International Self-Care Day was established by the International Self-Care Foundation (ISF) in 2011 to promote self-care as an essential component of health and wellbeing. The Foundation’s work has helped provide a practical vocabulary for understanding self-care not as a single behaviour, but as a broad and multidimensional set of capabilities and practices.

In 2026, International Self-Care Day also marks the culmination of the World Health Organization’s Self-Care Month, held from 24 June to 24 July. The 2026 theme – “Self-Care puts your health in your hands: Test. Track. Thrive” – encourages people to understand their current health, monitor meaningful changes and use that knowledge to take appropriate action.

Yet International Self-Care Day should prompt us to consider a broader question: how do we move from viewing self-care principally as a personal practice to recognising it as an essential component of public health?

Self-care is more than “looking after yourself”
Self-care is sometimes presented narrowly through the language of rest, relaxation and personal wellbeing. These activities may be valuable, but they represent only one small part of a much wider concept. The World Health Organization distinguishes between everyday self-care actions, such as healthy eating, physical activity, sleep and maintaining social connections, and self-care interventions, including diagnostic tests, monitoring devices and appropriate medicines. Understood in this broader way, self-care includes:
• developing the knowledge and confidence needed to make informed health decisions;
   • adopting health-promoting behaviours;
   • recognising and responding appropriately to symptoms;
   • managing minor ailments safely;
   • using medicines and health products responsibly;
   • monitoring an existing condition;
   • maintaining social and psychological wellbeing;
   • avoiding or reducing preventable risks;
   • knowing when self-care is appropriate, and when professional care is required

Self-care is therefore neither an alternative to healthcare nor a justification for withdrawing services. At its best, it is part of a connected continuum in which individuals, families, communities, professionals and health systems work together.

The seven pillars of self-care
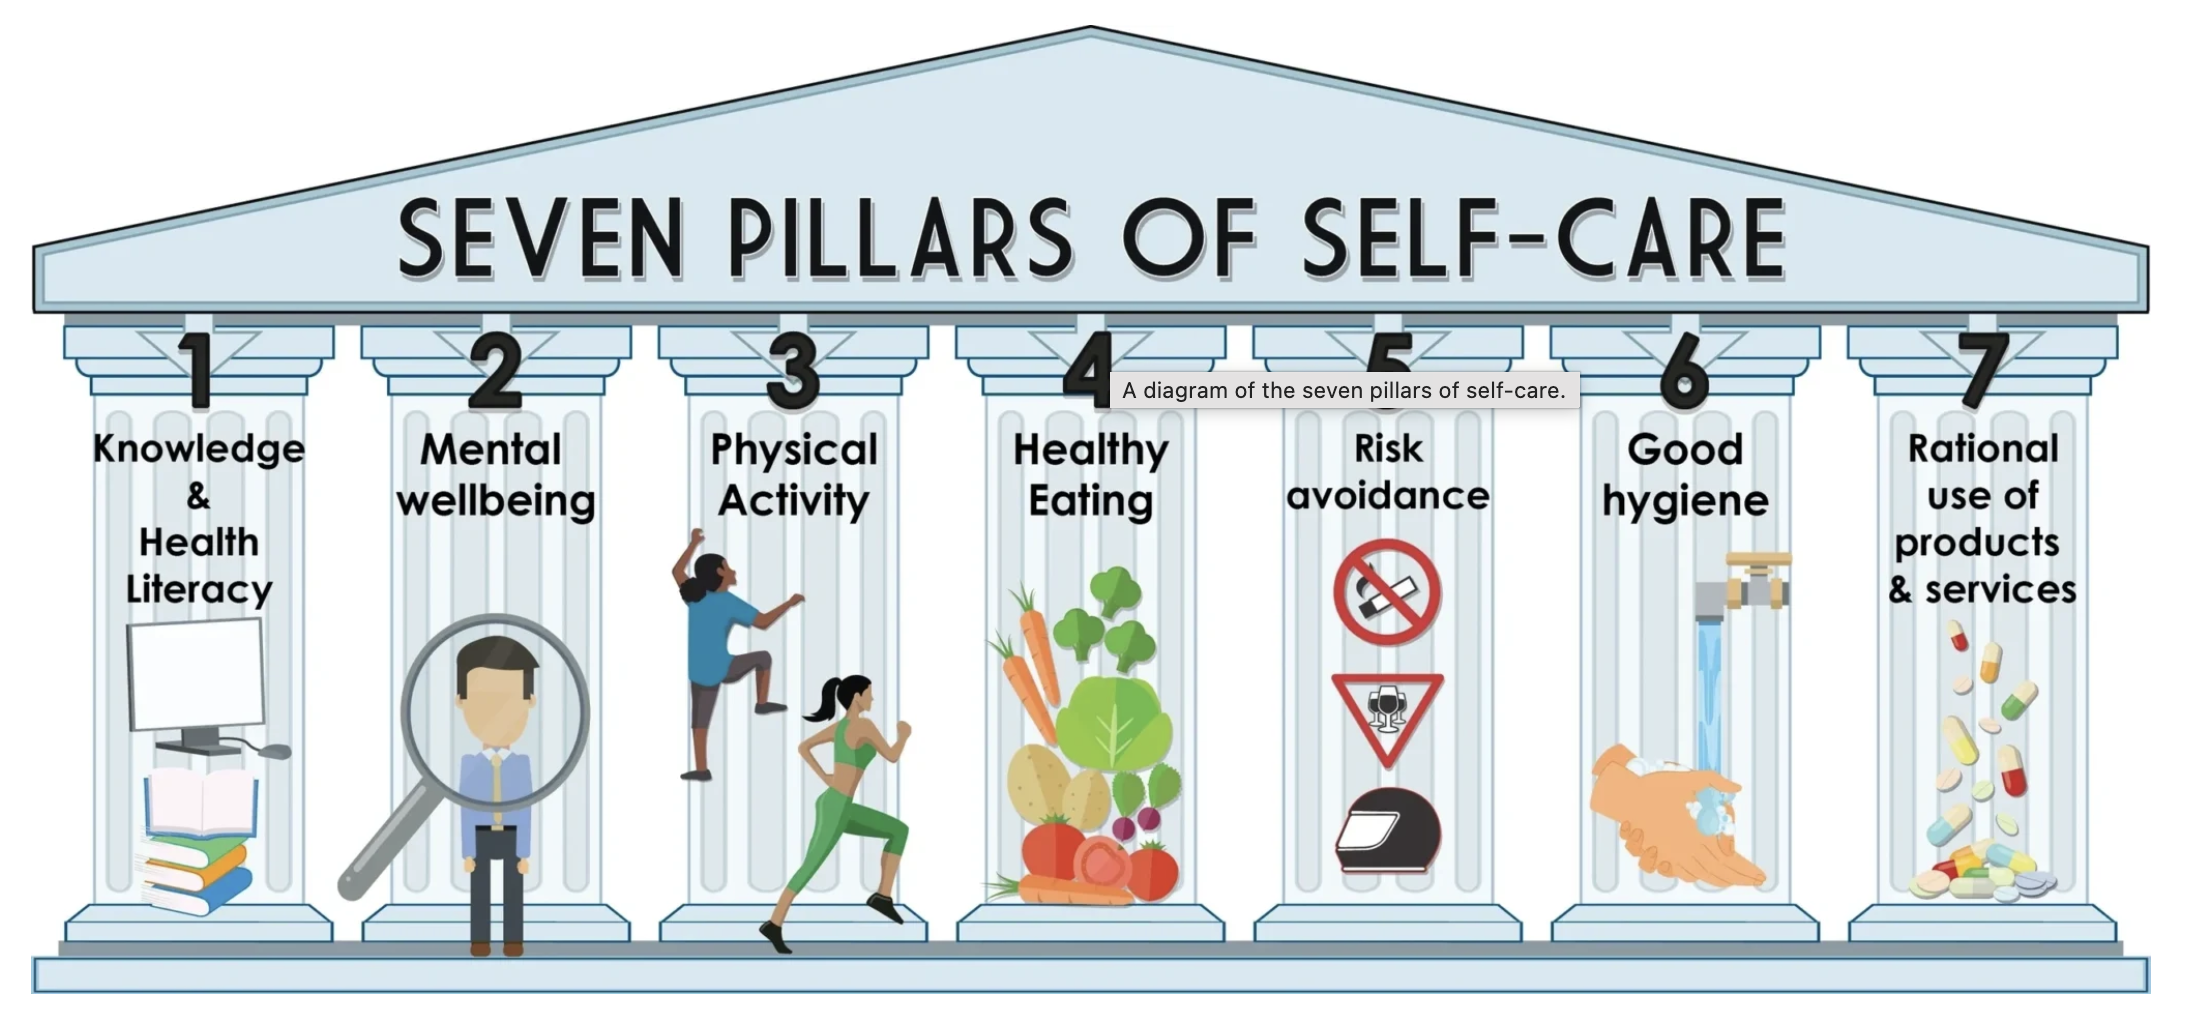
One of the International Self-Care Foundation’s most influential contributions is its Seven Pillars of Self-Care framework. The framework recognises that effective self-care depends on several interconnected domains rather than on a single lifestyle choice or intervention. The seven pillars are:
   1. Knowledge and health literacy
   2. Mental wellbeing, self-awareness and agency
   3. Physical activity
   4. Healthy eating
   5. Risk avoidance and mitigation
   6. Good hygiene
   7. Rational and responsible use of self-care products and services


Together, these pillars provide a useful bridge between individual action and public-health practice and make clear that self-care is considerably more substantive than the popularised idea of occasionally “treating yourself.” It encompasses the knowledge, behaviours, resources and judgement required to protect health throughout everyday life.

Health happens beyond the clinic
Modern healthcare systems are often organised around consultations, treatments and clinical episodes. However, health itself is shaped predominantly outside healthcare settings. It is shaped in homes, schools, workplaces, pharmacies, supermarkets, community organisations and neighbourhoods. It is affected by daily routines, social relationships, environmental conditions and access to trustworthy information. People continually interpret symptoms, assess risks and make decisions that may influence their present and future health.

Self-care is where prevention becomes actionable in everyday life. Primary prevention may involve healthy eating, physical activity, maintaining social connections or avoiding tobacco. Secondary prevention may involve noticing a change, using an appropriate test, monitoring blood pressure or seeking timely advice. Tertiary prevention may involve managing medicines, monitoring symptoms and adapting daily life while living with a long-term condition.

The seven pillars operate across this entire prevention continuum. Health literacy can support early symptom recognition. Mental wellbeing and agency can influence whether someone feels able to seek help. Physical activity, healthy eating and risk mitigation contribute to disease prevention. Hygiene can reduce communicable disease transmission. Responsible use of products and services can support safe management while reducing avoidable harm.

These activities rarely occur in isolation since they are influenced by family members, peers, healthcare professionals, community networks, commercial environments, digital platforms and public policy. This is why self-care should be treated not merely as a private behaviour, but as part of the infrastructure of prevention.

From a day of recognition to a 24/7 commitment
International Self-Care Day is a useful reminder that health does not begin when someone enters a clinic, nor does it end when they leave. Self-care is practised 24 hours a day, seven days a week—but the responsibility for enabling it must be shared.

Individuals have an important role in protecting and managing their health. Healthcare professionals have a role in supporting safe and informed decisions. Communities can provide connection, knowledge and practical support. Researchers and organisations such as the International Self-Care Foundation can provide frameworks, evidence and tools. Governments and institutions must create conditions in which the seven pillars of self-care are realistic, equitable and evidence-informed.

The transition from personal practice to public health requires us to stop treating self-care as an optional addition to healthcare. It should instead be recognised as one of the principal ways in which prevention is understood, supported and enacted in everyday life..

On International Self-Care Day 2026, the challenge is not simply to ask people to do more for themselves. It is to build systems and communities that enable everyone to participate meaningfully in their health—across all seven pillars, every day and at every stage of life. Self-care is practised individually, but it must be enabled collectively

Celebrating the life of Dr David Webber OBE
This year, ISD 24/7 also brings a moment of reflection following the death of David Webber OBE, a longstanding champion of self-care and an influential figure in the development of the International Self-Care Foundation. His commitment to advancing self-care as a serious public-health priority helped shape the field and inspired many of those working within it. To honour his contribution and sustain that legacy, the Foundation is instituting anthe Annual David Webber Self-Care Lecture, creating a continuing platform for leadership, evidence and debate on the future of self-care.

Prevention by Design: A Declaration on Self-Care & Lifestyle Medicine

Health systems across the world are facing unprecedented pressures. Populations are ageing, the prevalence of long-term conditions continues to rise, healthcare workforces are under increasing strain, and the costs of treating preventable illness continue to escalate. Despite decades of evidence demonstrating that many chronic diseases are preventable, healthcare systems remain largely organised around treating illness rather than preventing it. This imbalance is no longer sustainable.

The Self-Care Academic Research Unit (SCARU) and the International Self-Care Foundation (ISF) believe the next evolution of healthcare must place prevention where it belongs: at the centre of health systems. That belief has led to the development of the Declaration on Self-Care and Lifestyle Medicine, a consensus framework that sets out how health systems can better integrate prevention, behavioural healthcare and person-centred care. The Declaration, together with the accompanying scholarly paper, is scheduled for publication in the Self-Care Journal in Autumn 2026.

Why another declaration?

Self-care and lifestyle medicine are often discussed together because they share a common goal: helping people live healthier lives. Yet they have largely evolved independently. Self-care focuses on empowering individuals, families and communities to maintain health, prevent disease and manage illness. Lifestyle medicine provides healthcare professionals with evidence-based approaches to address the behavioural risk factors that drive many chronic diseases.

Both fields have generated substantial evidence. However, translating that evidence into routine healthcare has remained difficult. The problem therefore is not a lack of scientific evidence, but lack of implementation. Further to the Declaration on Self-Care & Medical Leadership, another declaration that emphasises the role of self-care and the self-carer in lifestyle medicine is needed.

Understanding the implementation gap

Our work suggests that implementation depends upon three interconnected components. First, individuals need the capability to engage in self-care. This includes health literacy, confidence, skills and motivation. Second, health and care professionals need the capability and confidence to deliver evidence-based lifestyle interventions consistently during routine care. Third, health systems themselves must be designed to support prevention through commissioning, policy, workforce development and organisational infrastructure.

If any one of these components is weak, implementation becomes fragmented. Improving patient knowledge alone is unlikely to transform outcomes if clinicians lack training. Likewise, well-trained professionals cannot consistently deliver preventive care without supportive health systems. The declaration therefore argues that successful prevention depends upon simultaneously strengthening all three domains.

Introducing the Integrated Capability–Delivery–System Model

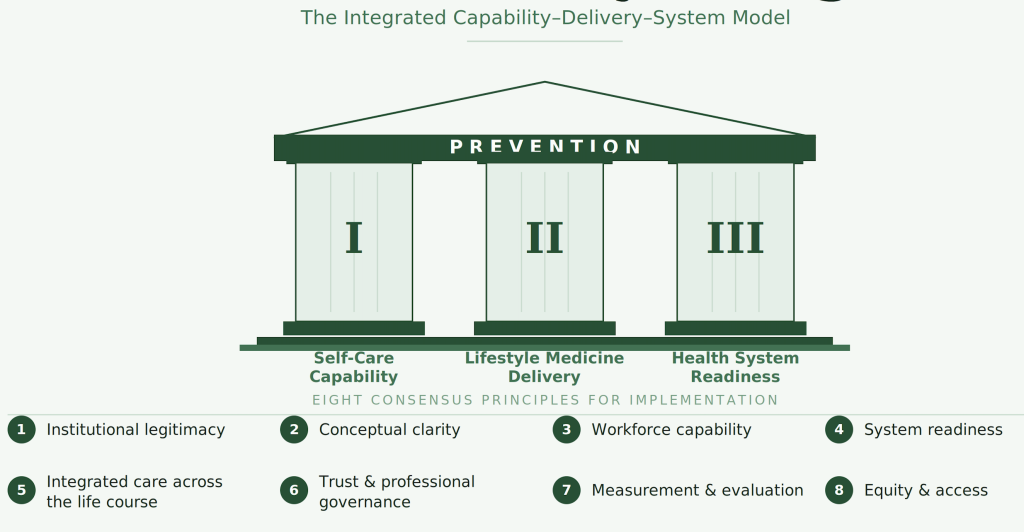
At the centre of the declaration is a new conceptual framework: the Integrated Capability–Delivery–System Model. The model proposes that effective prevention emerges from the interaction of three mutually reinforcing elements: (i) Self-care capability, (ii) Lifestyle medicine delivery, and (iii) Health system readiness.

Rather than viewing prevention as a collection of isolated interventions, the model conceptualises prevention as an integrated system. This systems perspective provides a practical way of understanding why so many well-intentioned prevention programmes struggle to achieve population-level impact despite strong supporting evidence.

Eight principles for implementation

The declaration proposes eight consensus principles to guide policymakers, healthcare organisations, clinicians and researcher: (i) Institutional legitimacy, (ii) Conceptual clarity, (iii) Workforce capability, (iv) System readiness, (v) Integrated care across the life course, (vi) Trust and professional governance, (vii) Measurement and evaluation, and (viii) Equity and access. Together, these principles move beyond simply encouraging healthier lifestyles. They describe the conditions required for prevention to become embedded within routine healthcare.

Why this matters now

Across health and care, there is growing recognition that preventing disease is both clinically effective and economically necessary. However, prevention cannot rely solely upon individual motivation. People require support whereas health and care professionals require training. Meanwhile, organisations require infrastructure and health systems require incentives that reward prevention rather than simply responding to disease once it has developed. This declaration argues that prevention should no longer be viewed as an optional addition to healthcare. It should be recognised as one of its defining functions.

Looking ahead

The Declaration on Self-Care and Lifestyle Medicine is intended as a starting point rather than an endpoint. It provides a shared framework that researchers, clinicians, commissioners, policymakers and patient organisations can use to align future work. Future research will continue to test, refine and operationalise the framework across different health systems and populations. As healthcare increasingly shifts towards prevention, integrated care and personalised medicine, developing coherent implementation frameworks will become just as important as generating new evidence. The challenge is no longer proving that prevention works but ensuring health systems are designed to deliver it.

The declaration is intended to catalyse new collaborations across academia, healthcare and policy. By promoting multidisciplinary research, producing high-quality scholarly outputs and strengthening international partnerships, we aim to advance the evidence base for self-care and lifestyle medicine, accelerate their integration into routine health and care, and ultimately improve population health outcomes at scale.